What Is the Anion Gap?
The anion gap is a calculated value that helps assess acid-base status by examining the main measured electrolytes in a blood sample. It is often obtained from a serum chemistry panel or other serum electrolytes results, using the relationship between sodium, chloride, and bicarbonate. Clinically, it is used to identify whether there are unmeasured anions contributing to an anion deficit and an underlying acid-base disorder.
In simple terms, the anion gap is a diagnostic tool that estimates the difference between positively charged and negatively charged particles in the blood. That difference reflects electrolyte balance and can point to a metabolic disturbance that is not obvious from the individual values alone. Because it is based on routine blood chemistry, it is often used as a screening test during patient assessment.
Most modern labs provide the ingredients needed for the calculation as a standard laboratory result. Even though the concept sounds abstract, the practical use is straightforward: if the gap is elevated, clinicians think about causes of metabolic acidosis, especially high anion gap metabolic acidosis.
Anion Gap Formula Without Potassium
The most commonly used formula without potassium is as follows:
Anion gap = sodium - (chloride + bicarbonate)
This formula uses sodium value, chloride value, and bicarbonate value measurements from the lab. If you're using an Anion Gap Calculator, this is usually the default method because it is more straightforward and matches common medical practice.
These values are generally reported in mEq/L. The formula takes away the combined amount of chloride and bicarbonate from sodium. Since sodium is the principal measured cation in the panel, and chloride plus bicarbonate are the main measured anions, the result approximates the space left by negative charge from unmeasured substances.
Although some older formulas also included potassium, many clinicians omit it because the contribution is small and does not usually change the practical clinical interpretation. A simplified formula makes the calculation simpler without sacrificing much utility in routine use.
If you check the result manually, make sure the units match and that the numbers come from the same test values set. An error in units or transcription can affect the result significantly.
Step-by-Step Math Demo
This is a basic worked example based on standard lab values:
- Na = 140 mEq/L Cl = 102 mEq/L HCO3 = 24 mEq/L
With the equation:
Anion gap = 140 - (102 + 24)
Start by add chloride and bicarbonate:
102 + 24 = 126
Then deduct from sodium:
140 - 126 = 14
This anion gap result is 14 mEq/L. Depending on the lab reference range, this may be viewed as normal or mildly elevated. That is why the result must always be interpreted within the clinical context rather than as a stand-alone number.
Using an anion gap calculator can minimize arithmetic mistakes, but the manual method is easy to check. The key is to remember the exact method and to use current lab values rather than outdated results. When values change rapidly, the gap can shift along with the patient’s acid base status.
Normal Values and Meaning
A expected anion gap depends on the laboratory reference interval, the measurement method, and whether potassium is included. In many settings, a usual non-potassium result is roughly in the low teens, but the exact reference interval varies from one lab to another. Always compare the number with the lab’s stated range instead of relying on a universal cutoff.
A high anion gap suggests extra unmeasured acids in the blood. This pattern is commonly associated with metabolic acidosis, especially anion-gap metabolic acidosis. The finding can help refine the differential diagnosis, but it does not identify the cause by itself.
One important factor is albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear lower than expected. In those cases, clinicians may use an albumin-corrected anion gap to get a more accurate corrected value. This is especially useful when evaluating a suspected acid-base disorder in patients with hypoalbuminemia.
Interpretation should also distinguish high-gap from normal-gap metabolic acidosis. A normal gap does not rule out acidosis; it may indicate bicarbonate loss with a compensatory rise in chloride, as seen in normal-gap patterns. That is why the number should always be interpreted alongside the full chemistry panel and the broader clinical picture.
Why Potassium Is Often Left Out
Potassium is often excluded because its concentration is significantly lower than sodium, and the difference usually has little impact on everyday clinical practice. The simplified formula improves consistency and speeds up use in busy settings. Many forms of laboratory reporting also leave out potassium for this reason.
From a practical standpoint, leaving potassium out makes the calculation easier to remember and minimizes the chance of error. The change in result is typically minor enough that it does not alter the general conclusion, especially when the goal is basic screening rather than advanced analysis.
That said, the omitted-potassium method is not a different concept. It is the same physiologic idea, just a streamlined approach built into many calculators and lab systems. If an older source includes potassium, the resulting number will be marginally higher, but the overall assessment of acid-base status often stays similar.
In other words, the anion gap calculator commonly used in practice is based on the streamlined formula because it is practical, reliable, and sufficient for most patient assessment scenarios.
Causes of a Elevated Anion Gap
A raised result indicates additional acid or undetected anions in the bloodstream. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each of these can increase the gap for a separate reason, but all lead to an rise in unmeasured acids.
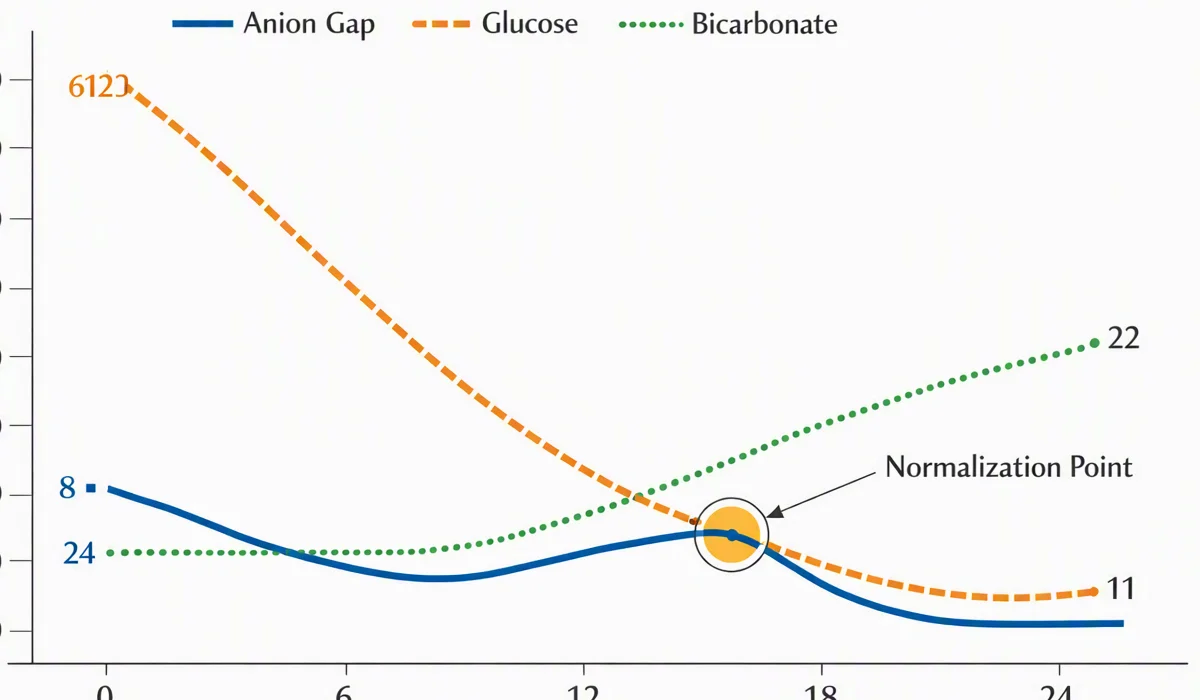
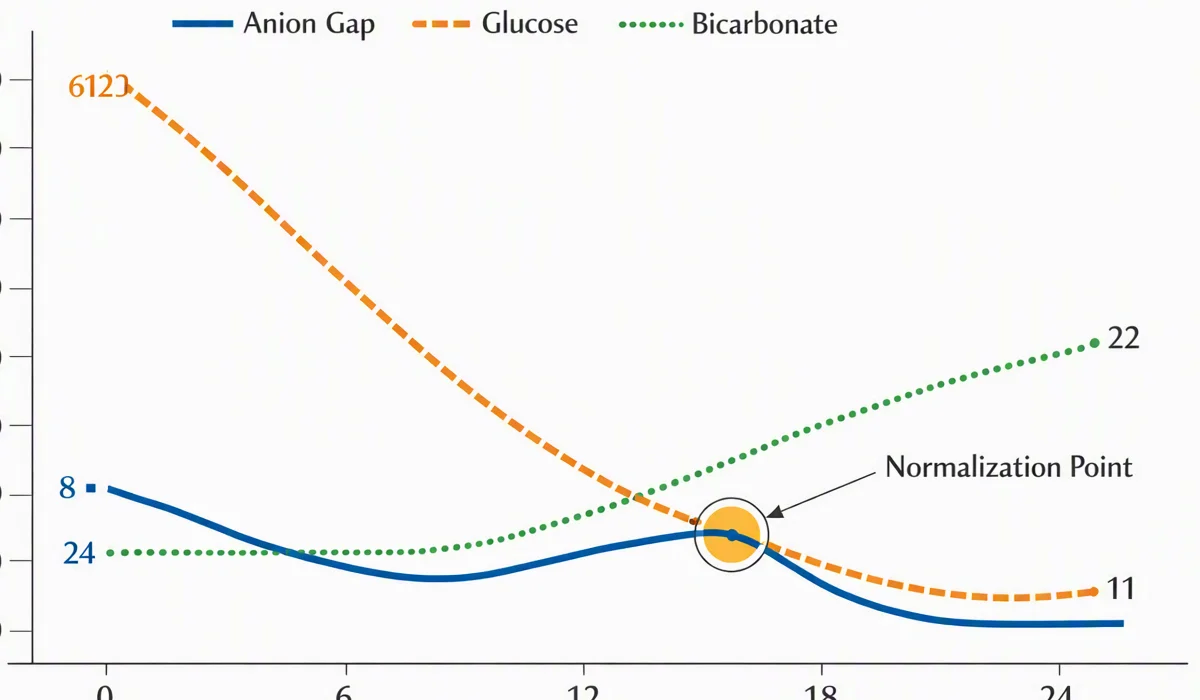
Lactic acidosis occurs when lactate builds up, often in settings of reduced perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis arises when ketones build up, such as in diabetes or prolonged fasting. Renal failure can reduce acid excretion, permitting acids to accumulate. Toxic ingestions may expose the body to substances that are metabolized into acids or that interfere with normal metabolism.
These causes are especially important important when the anion gap is elevated with signs of metabolic acidosis. A clinician may view the gap as a clue, then pair it with history, physical findings, and additional testing to identify the underlying problem. The gap itself is a indicator, not a final diagnosis.
Because different disorders can produce the same pattern, the value should be considered part of a wider diagnostic framework. A patient with high-gap acidosis needs a careful evaluation, and the anion gap calculator can help flag the issue early.
Drawbacks of the Anion Gap Calculator
An anion gap calculator is useful, but it has key limitations. The main is albumin correction. Since albumin is a major contributor to the normal gap, low albumin can obscure a medically important elevation. Without adjustment, the result may look misleadingly normal.
Also, the number depends on the lab’s reference range. Various techniques, instruments, and reporting methods can yield different results, so a result that seems unusual in one lab may be acceptable in another. That is why interpretation should always be tied to the particular laboratory’s reference interval.
Third, laboratory error can skew the reading. Sample contamination, processing delays, or transcription mistakes can affect sodium, chloride, or bicarbonate values. Since the gap is derived from these values, even one inaccurate test result can cause a misleading conclusion.
Finally, the calculation is only one part of the evaluation. It does not take the place of a thorough clinical review, arterial or venous blood gas when appropriate, or assessment for other causes of acid-base disturbance. If used well, it is a strong screening test; used alone, it can be limited.
Common Questions
How do you calculate anion gap without potassium?
Use the formula the formula sodium - (chloride + bicarbonate). This is the standard simplified method and is what how most anion gap calculator calculators use. Type in the lab values in mEq/L and take away the sum of chloride and bicarbonate https://anion-gap-help734.huicopper.com/how-to-use-an-anion-gap-calculator-for-hyperchloremic-acidosis from sodium.

What is the formula for an anion gap calculator without potassium?
The formula is anion gap = sodium - (chloride + bicarbonate). It takes the primary serum electrolytes from the blood chemistry panel and excludes potassium for simplicity. This is the most widely used calculation formula in regular use.
What is a typical anion gap when potassium is left out?
The reference values are based on the lab’s normal range and measurement method. Many labs consider a slightly elevated result normal when potassium is excluded, but you should always compare the number to the reported lab range on that specific lab result.
Why is potassium often left out of the anion gap calculation?
This electrolyte is usually excluded because it contributes only a small amount to the overall result. Leaving it out creates a streamlined formula that fits common day-to-day practice and laboratory reporting standards without meaningfully changing everyday clinical interpretation.
What does a high anion gap mean clinically?
A high result suggests additional unmeasured acids and is often associated with acid-base disturbance, especially high anion gap metabolic acidosis. Common causes include elevated lactate states, diabetic ketoacidosis, renal impairment, and poisoning. The value supports evaluation, but the cause requires further workup.